Medical Accounts Receivable Management for Small Practices
Structural changes in claims processing now demand disciplined AR workflows.

Accounts receivable management for a small medical practice now runs through a denial environment that has changed structurally, not temporarily. The forces behind that shift, payer AI adjudication, new CMS interoperability rules, and a Medicare Advantage denial rate that outpaces traditional Medicare, mean that a practice without dedicated denial-management capacity needs a disciplined, stage-by-stage AR process more than it needs a bigger billing staff. This piece maps that process end to end: how claims move from eligibility check to payment posting, where small practices lose revenue at each stage, and what a working system looks like at the points that matter most.
Why AR Management Has Gotten Structurally Harder for Small Practices in 2026
Three forces are now operating on claims at the same time, and each one makes the others more costly. Payer adjudication systems increasingly run on natural-language processing that compares a clinician's documentation against the codes submitted on a claim. Vague medical necessity language, or a chart that omits a relevant comorbidity, can trigger an automatic denial before any person at the payer ever looks at the file.
At the same time, federal rulemaking has changed the mechanics of prior authorization itself. The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) carries operational provisions that took effect January 1, 2026, and it reshapes how Medicare Advantage plans, Medicaid (both fee-for-service and managed care), CHIP, and ACA marketplace plans handle PA decisions. Standard requests must now be decided within 7 calendar days, and urgent requests face a shortened timeframe, though those specific decision clocks apply only to Medicare Advantage, Medicaid, and CHIP; qualified health plans on the federal exchanges answer to new denial-reason and reporting requirements without the same decision deadlines. Every denial under the rule must now state specific clinical reasons. A practice that hasn't built an API-enabled workflow to receive and act on that information faces new compliance exposure on top of the existing denial burden.
Traditional Medicare has changed too. The CMS WISeR Model, live since January 1, 2026, brought prior authorization to Traditional Medicare Part B at a scale it has not seen before, covering services such as epidural steroid injections, cervical fusion, and skin substitutes across six states: New Jersey, Ohio, Oklahoma, Texas, Arizona, and Washington. Fee-for-service Medicare has required prior authorization for a narrow set of services before, but WISeR extends that requirement to outpatient services at a scale that is new for the program. Layered on top of all this, payers are concentrating their AI-driven audit activity on the claims with the most money attached: imaging, specialty drugs, surgical procedures. The claims worth the most to a practice's revenue are now the claims facing the highest denial risk.
None of this is a billing-department failure. The Commonwealth Fund's Affordability Survey found that a significant share of privately insured U.S. adults report being denied coverage for care their doctor recommended within the past year, a finding that places denials inside the normal operation of the reimbursement system. A small practice, typically defined here as one with fewer than five providers, meets this environment with none of the infrastructure a larger health system can build: no dedicated denial team, no payer-intelligence function tracking policy changes before they cause a spike, no early-warning system that catches a new payer rule before it has already generated a wave of denials. When one staff member covers both the front desk and billing, a denial that lands during a busy clinical day can sit untouched until the appeal window has narrowed or closed. None of that reflects poorly on the staff involved. It reflects a mismatch between the resources a small practice has and the resources this environment now requires, and that mismatch turns every weak point in the AR chain into a bigger problem than it would be for a larger group.
Closing the resulting gap is a matter of speed and payer-specific knowledge, both of which are hard for a small staff to maintain alone. Services like Altair Health that pair AI-driven claim handling with in-house expert billers exist specifically to close that gap, working a denial the moment it arrives rather than letting it sit in a queue until the appeal deadline has already narrowed. The rest of this piece maps the disciplines that make that kind of response possible, stage by stage, starting with how the AR cycle fits together as a single chain.
The AR cycle end to end
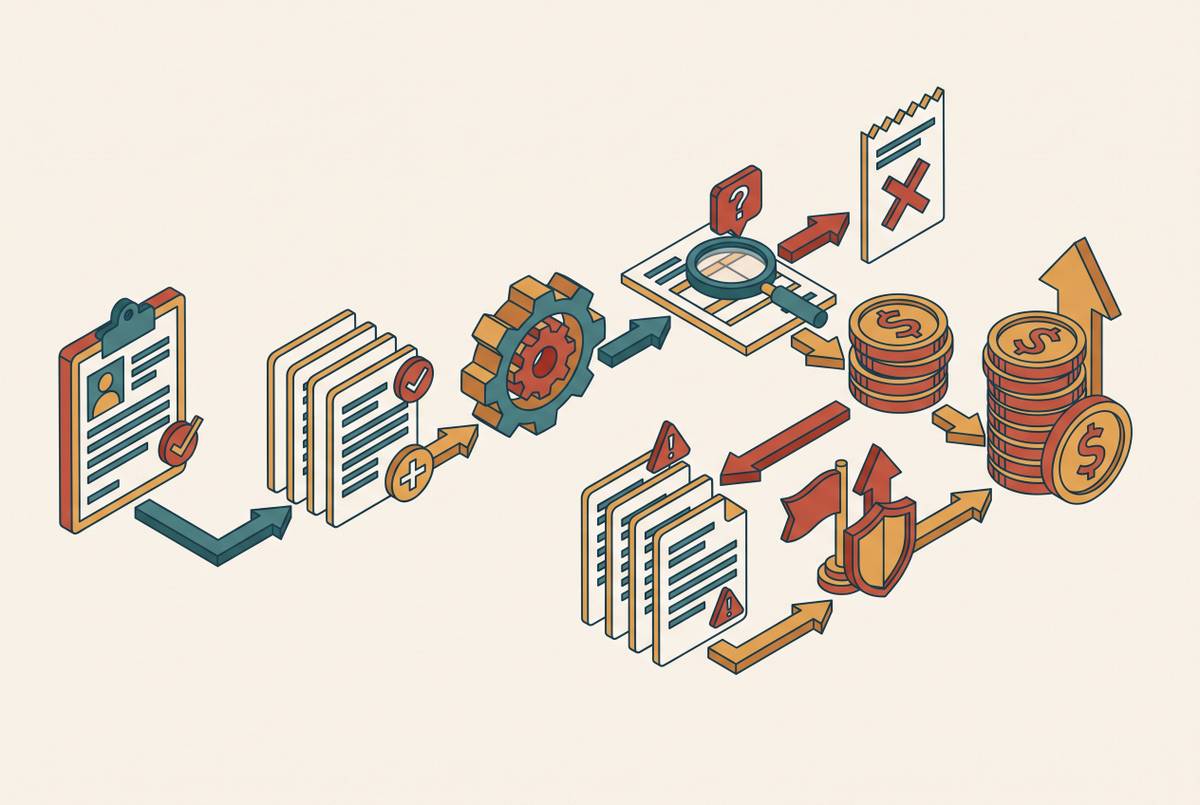
Accounts receivable management is a sequence of stages, each of which sets the conditions for the one after it: pre-visit eligibility verification, prior authorization where a payer requires it, claim scrubbing and submission, payer adjudication, denial management and appeals, payment posting, patient billing and collections, and finally AR monitoring and reporting.
Every hand-off in that sequence carries its own timing requirement. Eligibility has to be confirmed before the patient walks in the door. Prior authorization has to be locked down before the service is delivered. Claims have to go out within the payer's filing window. Denials have to be worked before the appeal deadline closes. Payment has to be posted promptly, because the longer it waits, the more it distorts the practice's picture of its own receivables.
The chain compounds. A missed eligibility check at the front end can produce a denial three stages later at adjudication. If that denial sits unworked for two weeks, it ages into a claim that is harder to recover, and if no one ever appeals it, the money is gone for good. The failure that finally appears in a month-end report was usually created weeks earlier, at a stage that looked low-stakes in the moment it happened, and structured AR workflows address this by categorizing denials the moment they come in, using Claim Adjustment Reason Codes (CARC) and Remittance Advice Remark Codes (RARC), so the practice can trace a denial back to its root cause before the claim ages any further.
A handful of metrics tell a practice whether this chain is actually working: days in AR, clean claim rate, first-pass resolution rate, denial rate, and net collection rate. Each one reflects a different point in the sequence. Days in AR is the number most practices watch, but it's a lagging indicator: by the time it climbs, several stages upstream have already broken down. Clean claim rate and first-pass resolution rate matter more for catching problems early, because they show whether issues are getting caught before submission. A practice that watches only days in AR is watching the damage after the fact, not the point where it started. The failure that eventually appears on a month-end report was set in motion weeks before anyone saw it, at a stage of the cycle that felt routine at the time.
What the benchmarks say about where small practices stand
Performance data on claims and denials shows a real gap between what a well-run practice can achieve and what most small practices are currently running, and that gap tracks to specific, identifiable points in the workflow.
Specialty-specific denial rates differ sharply from the aggregate number. Denial-rate benchmarks for 2026 show the widest spread in behavioral health, driven by how intensively payers require authorization for that care, and in orthopedic surgery, driven by the complexity of mental health parity law in the first case and by a prior-authorization-heavy payer mix in the second. Chiropractic and physical therapy practices tend to run elevated denial rates specifically where Medicare modifier logic breaks down, a failure that has a known fix rather than one that reflects some unavoidable feature of how payers treat those specialties. Primary care and internal medicine post the lowest denial rates among these cohorts, but even those practices sit well above what the best-performing groups in their specialty achieve. There's real recoverable revenue sitting even in lower-acuity practices that assume their numbers are already fine.
Payer mix changes the picture further. Medicare Advantage denial rates run above 17 percent, more than double the rate for traditional Medicare, so a practice with a heavy MA patient population faces a materially different AR challenge than its blended, practice-wide denial rate would suggest on its own. Two practices with identical aggregate denial rates can be facing very different underlying risk, depending on how much of their revenue runs through MA plans specifically.
The gap between a practice's current numbers and what best-in-class performance looks like is a gap in workflow discipline at specific, identifiable stages of the cycle, and the next two sections show exactly where those stages tend to break.
Why eligibility verification and prior authorization fail early
Most eligibility and prior authorization failures don't get caught at the front end because small practices still treat verification as something checked once, at scheduling, rather than as a real-time process repeated at every encounter. That distinction matters more now than it used to. Medicaid redeterminations and shifts in ACA subsidy eligibility are moving patients in and out of coverage in the middle of the year. A patient confirmed eligible at the time of scheduling can show up for an appointment with coverage that's already lapsed. Verifying eligibility only once, well before the visit, is no longer enough to catch that.
Prior authorization failures work differently, and they carry a particular kind of damage. The service gets delivered, the PA was either never confirmed or had already expired, and the denial doesn't arrive until weeks later, for care that's already been provided and can't be undone. That timing gap is part of what makes PA failures so costly: by the time the practice learns there's a problem, the only options left are to appeal or write the revenue off.
The PA burden itself is already heavy before any of these failures happen. The AMA's Prior Authorization Physician Survey found that the average practice spends roughly 13 hours a week managing prior authorization requirements, time that's already stretched thin before an avoidable error adds an appeal on top of it. When a PA request is denied, the most common reason payers cite across major commercial insurers is "not medically necessary," followed by incomplete step therapy documentation and denials coded as "experimental or investigational."
CMS-0057-F changes part of this picture by requiring payers to publish their PA requirements through standardized electronic interfaces, so a practice equipped to query those systems electronically can look up a payer's coverage criteria before a service is ever scheduled. A practice that isn't equipped for that kind of workflow faces both the compliance exposure built into the new rule and a higher baseline denial rate, because it's still working from outdated or incomplete information about what a given payer actually requires.
One of the more avoidable failures in this part of the cycle has nothing to do with clinical judgment. Many large insurers delegate prior authorization review to a separate utilization management vendor, and when a PA request is denied under that arrangement, the appeal has to go to the vendor, through that vendor's own portal or fax line, not to the health plan directly. A practice that files the appeal with the insurer instead of the delegated vendor can lose that appeal purely on a procedural technicality, before a single clinical reviewer ever reads the record. Small practices without a current map of which payers delegate which services to which vendors will file in the wrong place repeatedly, losing appeals on paperwork rather than on the medical facts, a failure that is entirely preventable with the right routing information on hand.
Every one of these front-end gaps sets up the next stage for failure. A claim that reaches submission with eligibility unresolved or a PA still unconfirmed is already in trouble before a biller ever opens the file, regardless of how clean the claim itself looks on paper.
Where claim scrubbing stops denials before submission
Claim scrubbing software catches a specific, well-defined category of problem: format and technical errors. It does not catch the second category of failure that's become more common as payer AI systems have gotten better at reading clinical documentation against the codes attached to it.
What scrubbing reliably stops before a claim goes out: missing National Drug Code numbers, an incorrect place-of-service code, a missing revenue code, or a mismatch between the demographic information on the claim and what's on file in the eligibility record. Those are structural problems, and a scrubber built on a standard edit library finds them reliably.
What a scrubber cannot catch is harder to systematize. Clinical documentation that doesn't explicitly establish medical necessity in the language a payer's system is scanning for will pass every format check and still get denied at adjudication. A modifier can be entirely valid in form and still be wrong for a specific payer's rules. Code pairs can conflict with a payer's own bundling policy even when nothing in a generic edit library flags the combination. Payer NLP systems are now built to compare the actual language in a clinical note against the codes submitted at the time the claim is adjudicated, so a technically clean claim with a thin or vague note can still be denied automatically, even where the care delivered was appropriate and the code itself was correct.
A narrower, more mechanical set of modifier errors accounts for a large share of denials that have nothing to do with documentation quality at all, and these are entirely correctable. A screening colonoscopy that turns diagnostic mid-procedure needs a specific modifier attached, PT for Medicare and modifier 33 for commercial payers, and using the wrong one triggers an automatic denial regardless of whether the PA was in order. A Medicare chiropractic claim missing its AT modifier is an automatic denial. A physical therapy claim that crosses the therapy cap threshold without its KX modifier fails the same way. None of these are gray areas of clinical judgment. They're known rules with known fixes, and they generate denials only because the billing workflow has no built-in step that flags them before the claim goes out the door.
Because each stage of the AR cycle feeds directly into the next, a practice needs visibility into every claim and every dollar as it moves from eligibility through authorization, submission, adjudication, and payment, not a single monthly report that arrives once the window to fix anything has already closed. An AI-powered medical billing service built to integrate with a practice's existing systems and clearinghouse can track each claim in real time and surface a failure at the moment it happens, rather than leaving a practice to discover it during month-end reconciliation, weeks after the appeal deadline has already started to close.