Healthcare Revenue Cycle Flowchart for Physician Practices
Registration errors and eligibility gaps drive more denials than coding mistakes ever will.
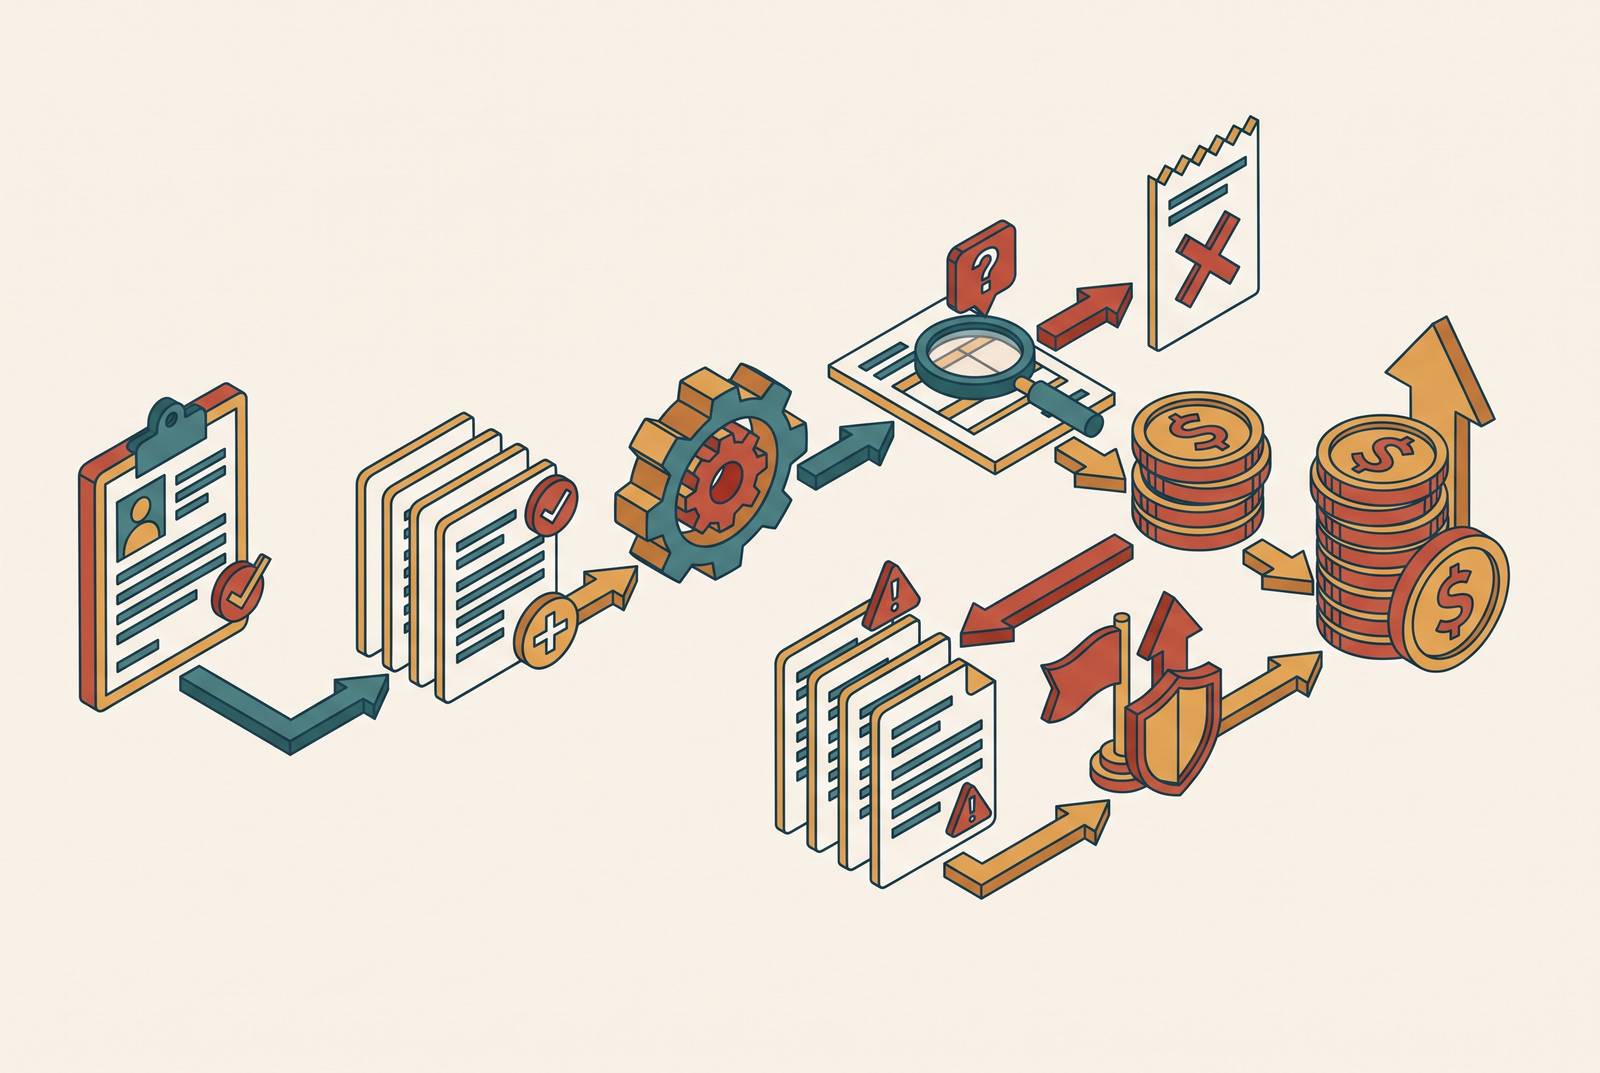
Most revenue cycle flowcharts get drawn as a straight line: schedule the patient, verify insurance, submit the claim, post the payment. That picture is wrong, and the mistake costs real money. The cycle loops back on itself constantly. Denials send claims back to steps everyone assumed were finished, and every stage doubles as a place where revenue either gets protected or quietly disappears. Read correctly, the flowchart is a map of where denials enter and where recovery is still possible, and the stage that deserves the most blame isn't the one most practices watch.
Start with the reference sequence anyway, because it's the shared vocabulary billing teams use to talk to each other. Patient scheduling and registration comes first, then insurance eligibility verification, then prior authorization, then the clinical encounter and its documentation. From there: claim generation and scrubbing, submission to the payer or clearinghouse, adjudication and remittance, denial management and appeals, patient billing and collections, and finally payment posting and AR reconciliation.
Treat this as a chain of dependencies. Each stage hands its output to the next, and a flaw at any point doesn't stay where it started. A registration error doesn't announce itself at registration. It appears three weeks later as a denial, long after anyone remembers the intake call where it happened.
Group the stages by when a problem is still fixable, and the picture sharpens. Registration through scrubbing is pre-claim: everything here is preventable, in theory, before a claim ever leaves the building. Submission through adjudication is in-flight, the claim is out of the practice's hands and subject to payer judgment. Denial management through AR close is post-adjudication, plain damage control, and the questions asked there differ from the ones asked upstream. No single number captures performance across all three phases. A practice can post a clean claim rate that would make any biller proud and still bleed money in AR follow-up. A fast payment turnaround can sit right on top of a rising denial rate nobody's tracking.
Where denials enter: the front-end stages from registration through prior authorization
Most people blame coding or payer stinginess for denials. They're wrong. Registration and eligibility errors drive the largest share of preventable denials, and inaccurate patient registration alone accounts for roughly a fifth of preventable denials. That dwarfs any single mid-cycle error type, and it's the stage furthest from where anyone thinks to look, because registration feels clerical next to the clinical and billing work downstream. That is exactly backwards, given that registration feels clerical next to the clinical and billing work downstream even though it is the single biggest blind spot in front-end revenue cycle work. It's the single biggest blind spot in front-end revenue cycle work, and practices that keep staffing coders instead of registration staff are solving the wrong problem.
Eligibility verification fails for a structural reason: coverage confirmed at scheduling is not the same as coverage on the date of service. Plans change. Deductibles reset. The order of coordination-of-benefits shifts the moment a patient picks up a second policy. Verifying once, at scheduling, and calling the job done is the most common mistake in this part of the cycle. The standard that actually holds up is real-time verification at multiple checkpoints, at scheduling, the day before, and again the day of service, because any one of those windows can catch a change the others missed. When verification fails anyway, the timing is brutal: the denial does not appear until weeks later, long past the point where anyone could have collected an upfront payment or rescheduled the visit.
Prior authorization compounds the problem differently. Physicians and their staff lose a real chunk of the week to PA paperwork, and each submission and status check eats several minutes on its own, minutes that stack up fast across a full patient panel. A missed or expired authorization behaves exactly like a bad eligibility check: invisible until after the claim goes out, at which point the service has already happened and there's no upfront fix left. Payers have shifted the burden rather than reduced it. Initial denials tied directly to prior authorization dropped somewhat in 2024, while medical necessity and request-for-information denials both rose over the same period. The paperwork moved. It didn't disappear.
Everything at this stage comes down to one distinction: whether the practice catches eligibility and authorization gaps before the patient is seen, or finds out from an Explanation of Benefits three weeks later.
Claim generation and scrubbing: the last internal checkpoint before a claim enters payer hands
Clinical documentation feeds claim generation directly, so a documentation gap becomes a billing error without anyone on the billing team making a separate mistake. The chart note and the claim aren't two different things produced by two different departments. They're the same information, translated.
Automated scrubbing catches a specific, limited set of problems: missing patient or insurance detail, mismatched procedure and diagnosis codes, invalid modifiers, eligibility inconsistencies that slipped past registration, payer-specific formatting quirks. It's good at format. It has no way to judge medical necessity, and it can't catch a payer-policy deviation that requires knowing what a specific payer will actually pay for, beyond what the claim form technically allows.
The industry benchmark for clean claim rate is 98%, so no more than two claims out of a hundred should need manual correction after first submission. Most practices don't hit that number, and that gap is the whole problem in miniature. Every claim that exits scrubbing with an error triggers a rework cycle, and rework cycles are what stretch out Days in AR. The two metrics move together by mechanism, not coincidence, because an error caught in scrubbing costs minutes, while the same error caught after payer rejection costs a resubmission, a follow-up call, and weeks of waiting.
What closes the gap clearinghouse edits leave open is payer-specific knowledge, and someone has to maintain it actively rather than set it once and forget it. Knowing that a particular payer wants a specific modifier combination, or rejects a certain place-of-service code without a matching clinical note, isn't something a scrubbing tool figures out on its own. A staff member has to track it and update it as payers quietly change their own rules. Everything downstream depends on one question: what share of claims exits clean, and is anyone tracking which error types keep coming back.
Adjudication and the denial spike: what happens once a claim is in payer hands
Once a claim leaves the practice, the numbers turn unforgiving. Initial denial rates have been climbing, landing well above the 5% mark considered the outer edge of acceptable performance, and far above the sub-3% range that counts as best-in-class. That climb isn't evenly distributed. Medical necessity denials and request-for-information denials have both risen, and the increase in those two categories outpaces whatever ground was gained by fewer prior-authorization denials. Clinical denial rates kept climbing into the following year, and the average practice's success rate at overturning clinical denials on appeal slipped rather than improved.
A payer behavior shift explains the pattern. Payers pay clean, simple claims faster while subjecting complex or high-cost claims to sharper review. The pool of easily-paid claims is shrinking, and what's left is disproportionately the claims that need real appeal work.
Denial rates also vary by payer type. Medicare Advantage and commercial plans both post double-digit initial denial rates, with Medicare Advantage and commercial plans both posting elevated denial rates across categories. None of this happens in a vacuum a practice can plan around, either. Many payers require an appeal within 60 to 90 days of the initial denial, but the denial notification itself can take over a month to arrive, which compresses the real response window down to a few weeks at most. Payers also change clinical criteria and documentation requirements without warning, and often the first sign a policy shifted is a sudden spike in denials for a service that was being paid without issue the month before. Each denied claim adds processing cost on top of the lost or delayed revenue, cost that compounds across a practice's full claim volume.
The practices staying ahead of this track denials by payer and by category. The ones falling behind look at the aggregate number at month-end and assume that tells the whole story. The aggregate number at month-end doesn't tell the whole story.
Denial management and appeals: where most recoverable revenue is abandoned
More than half of denied claims that are worked get overturned, according to available data on denial outcomes. That single fact should reframe how a practice thinks about a denial. Most denied revenue isn't lost, it's recoverable, and treating a denial as a dead end is simply wrong.
The recovery rate collapses anyway, because most denials never get worked in the first place. A large share of denied claims are never appealed at all, which makes non-appeal the single biggest source of avoidable revenue loss in the entire cycle. Not underpayment. Not bad contracts. Non-appeal. Denial rates keep climbing year over year at most practices, and only a small fraction report any improvement, because the practices falling behind aren't filing appeals badly. They're not filing them.
The reasons are operational. Denial queues often get reviewed at month-end instead of as claims come in, and by month-end some appeal deadlines have already passed. Staff turnover erases the institutional memory of which payers respond to which appeal format, so every new hire relearns the same lessons from zero. Most practices don't prioritize by dollar value, either: a $500 denial sits in the same queue position as a $14,000 one, and the smaller one often gets worked first simply because it's easier to close. Denials skew toward higher-cost treatments, which means the unworked pile often carries a disproportionate share of total dollars at risk.
Appeal quality matters as much as appeal volume. A generic reconsideration letter underperforms one that addresses the specific denial reason with the right documentation attached, whether that's clinical evidence for a medical necessity denial or the exact missing document for an RFI denial. What matters here is what share of denials gets appealed, what the overturn rate looks like by denial type, and how much time passes between denial receipt and appeal submission.
Patient billing and AR follow-up: the tail of the cycle that erodes collections
Patient balances collect at a fraction of the rate payer balances do, typically somewhere in the 34 to 48% range, and the gap keeps widening rather than closing. Practices are collecting less per dollar owed by insured patients than they were a year earlier, and the trend worsened further the year after that. Bad debt as a share of receivables has crept up alongside it.
Days in AR is the metric that summarizes how the whole cycle performed, and it's the one number worth checking first. The industry average runs 40 to 45 days, with high performers keeping it under 35, and the accepted rule is that AR aged past 90 days should stay below 10% of total receivables, because collection probability drops sharply once a claim crosses that line. True AR days have been rising, and the increase reflects two things stacking on top of each other: denial rework dragging claims backward, and patient collections slowing down at the same time.
Some of the erosion is self-inflicted. Underpaid claims get accepted without follow-up more often than anyone would like to admit, and payer-allowed amounts often run well below independently verified market rates for the same service in the same region, so a claim can get "paid" and still represent a quiet loss. Patient statements often go out once, with no systematic second or third attempt, and balances age into bad debt simply because nobody followed up. AR also rarely gets worked by risk: staff tend to chase the easy balances rather than the largest or oldest ones. What matters is a practice's Days in AR, what share sits past 90 days, and the point at which a collectible balance quietly gets written off as if it never existed.
Reading the flowchart as a denial-risk map: what the metrics reveal about where the cycle is breaking
No single metric tells the whole story. The value comes from reading several together, because the combination points to exactly where the cycle is breaking.
A high denial rate paired with a strong clean claim rate means the scrubber is doing its job, but the errors slipping through are payer-policy mismatches the scrubber was never built to catch. A low denial rate paired with a long Days in AR means denials are being prevented upstream, while unworked balances or slow follow-up stall money that should already be in the bank. A high denial rate combined with a low clean claim rate and a long Days in AR points somewhere else entirely: the damage started at registration or documentation, and it's compounding at every stage after that. An acceptable denial rate sitting next to a weak net collection rate means claims are getting paid, but patient balances or underpayments are quietly eating the yield.
Net collection rate ties this together. The typical range runs between 90 and 95%, with high performers above that, and anything below 90% signals revenue escaping across more than one stage at once. Cost to collect works as a second check: a well-run practice spends somewhere around 3 to 4% of net patient revenue collecting what it's owed, while typical billing and RCM costs across the industry now run closer to 5%. A practice spending above that mark while underperforming on collections is paying more to collect less, about as clear a signal of a broken process as the numbers get.
None of this holds still, either. Payer behavior is a moving variable. Medical necessity and RFI denial rates have both climbed, and clinical denial rates kept rising into the following year. A practice whose metrics looked fine two years ago may carry a materially worse denial profile today without having changed a single internal process. The flowchart only earns its keep as a management tool when it's read as a set of pressure points that shift as payers shift, and that have to be watched continuously rather than checked once and filed away.
Sources
- Claims denial rates up, prior auth denials down in 2024: Report - Becker's Payer Issues | Payer News
- Payer Denial Tactics — How to Confront a $20 Billion Problem | AHA
- Providers missing out on more revenue due to payers' denials
- humanmedicalbilling.com
- A physician�s guide to effective revenue cycle management | AMA
- promantra.us
- gebbs.com
- experian.com