Billing Staff Turnover and Revenue Cycle Institutional Memory Loss
When billing staff leave, payers' hidden behavior patterns disappear with them.
It is a working map of how specific payers actually behave, built up over years of submitting claims, watching denials come back, and learning what to do differently the next time. Staffing shortages in revenue cycle management are now a structural condition of the industry, not a temporary hurdle to clear. They are a structural condition of the industry now, and front-office RCM teams are experiencing a staggering rate of departure as a result. The workload a departing biller carried can be redistributed among the staff who remain, at least for a while. The judgment that biller applied, built from years of watching one payer behave one way and another behave differently, cannot be redistributed, because no one else has it.
The strongest objection to this framing is that billing is a learnable process, not a rare talent, and a competent new hire can pick it up. That is true as far as it goes. Claims formatting, coding conventions, and basic payer rules can be taught in a few weeks. What cannot be taught on the same timeline is the specific, accumulated knowledge of how one payer's adjudication team actually behaves, as opposed to how its published policy says it should behave. That gap between stated policy and operational behavior is exactly where an experienced biller's value sits, and it only closes through repeated exposure over time. Nobody transfers that kind of knowledge in an exit interview.
What Institutional Memory Contains
Institutional memory in a billing operation is a detailed, payer-specific record of behavior that exists only inside one person's head, not general competence at submitting claims. It includes knowing which codes tend to trigger an automatic audit with a given payer, which documentation patterns reliably get a claim paid the first time versus kicked back for review, and which specific appeals language tends to move a denial to an approval. It includes knowing that one payer needs a modifier resubmitted in a particular format to clear, and that a particular adjuster at another payer denies almost everything on first pass but approves on appeal once the right paperwork lands. None of this lives in a manual or in the practice management system. It lives nowhere else but in the practitioner's memory, built claim by claim, denial by denial.
This is why the standard management response, which is to ask departing staff to document their processes before they leave, falls short of the actual problem. What gets written down is the outcome: a claim was denied, then resubmitted, then paid. What never makes it into any document is the behavioral logic that produced the fix, the specific judgment call about which modifier to add or which phrase to use in an appeal letter. That workaround knowledge disappears when the person who held it walks out the door.
The problem compounds because payers themselves are changing how they behave, not just what their policies say. Initial claim denials are projected to reach 12 to 15 percent in 2025 as major payers deploy AI adjudication systems that shift denial logic without updating any published policy. A biller's accumulated knowledge of how a payer actually behaves increasingly diverges from what that payer's written rules state, which makes the knowledge harder to replace with a document and more valuable when it exists in a person who has kept pace with the drift. At the same time, remote work has become a real differentiator in where billing professionals choose to work, and the people most likely to leave for a better remote arrangement are often the same people least anchored to a single practice's specific institutional context. Because the asset at risk is mobile, the practice has limited leverage to keep it in place once a better offer appears elsewhere.
A practice's own system holds a record of denial patterns, which seems like it should cover this gap, but the record only shows what happened, not why the fix worked. The reasoning that produced a successful resubmission is the exact thing that never gets typed into any field.
How turnover triggers a revenue cascade
The financial damage from a billing departure does not land all at once as a single, visible cost. The financial damage unfolds as a sequence, where each failure creates the conditions for the next one, and the losses accumulate for weeks before they appear in any report a practice administrator actually reads.
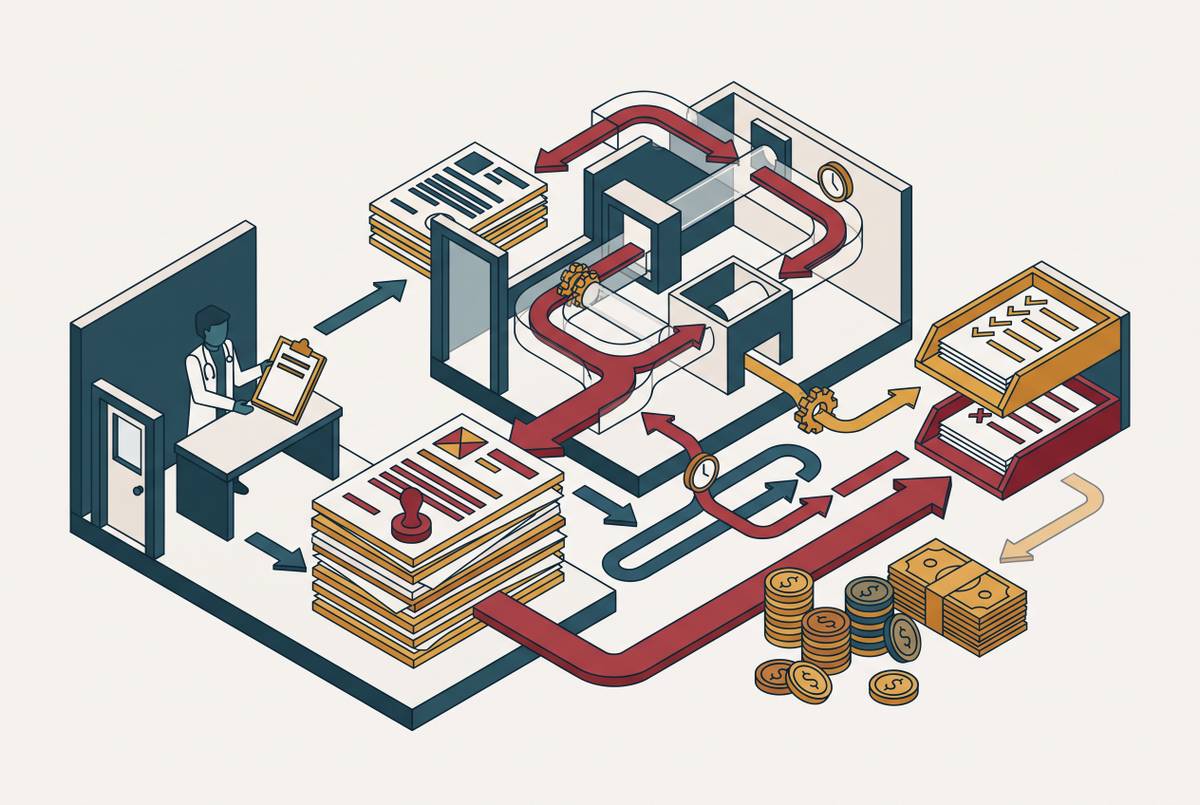
The seat empties first, and claims volume drops immediately as the remaining staff absorb a workload built for more people than are left to do it. Those remaining staff direct their attention to getting new claims out the door, because that is the visible, urgent task, which leaves no time to work the backlog of existing denials. With denials going unworked, the denial rate climbs, and MGMA data shows understaffed practices seeing denial rates rise well above the industry norm, against under 5 percent for offices that are fully staffed. As denials sit unresolved, accounts receivable ages, and older claims become progressively harder to collect the longer they sit. Eventually, without consistent follow-up, payers close out unworked claims entirely and keep the money, a loss that cannot be recovered once that window shuts.
Hiring a replacement does not stop the clock. New billing staff need real time to reach full productivity, and during that ramp-up period, claim processing slows further, denial rates tend to climb rather than recover, and the payer-specific knowledge the practice actually lost does not transfer through any onboarding checklist. The practice ends up paying twice: once in the direct cost of replacing the person, and again in diminished revenue cycle performance while the replacement learns, slowly and the hard way, what the previous biller already knew.
The replacement cost itself is not small. Industry analysis puts the cost of replacing a billing role at a significant fraction of annual salary, running as high as double that salary once recruiting, onboarding, and lost productivity are factored in. Set against a median biller salary that the Bureau of Labor Statistics places in a range where even a fraction of that replacement cost represents a serious financial hit, the arithmetic becomes difficult to ignore. And replacement cost is only the visible half of the ledger. A separate category of loss comes from claims that were never billed at all, or denials that were simply abandoned without an appeal because nobody had the bandwidth or the knowledge to pursue them. This kind of leakage does not appear in standard reporting until its cumulative effect becomes too large to miss.
The obvious response to a staffing gap is to triage: focus the remaining team's limited time on the highest-dollar claims and let the rest wait. But triage itself depends on the same payer-specific judgment that just left the building. An understaffed team stripped of that knowledge cannot reliably tell which claims are actually highest-risk or highest-value. Even the fallback strategy for surviving the gap requires the exact asset the gap created in the first place.
Payer Behavior in 2026
Practices are losing their most knowledgeable billing staff at precisely the moment payers have become more complex, more automated, and less forgiving of practices that cannot keep pace with behavioral changes that no official policy update ever announces.
Prior authorization has become a systematic pressure point across the industry. Major plans including UnitedHealthcare, Humana, Aetna, and BCBS have deployed AI adjudication systems that apply internal clinical criteria without an individual physician advisor reviewing the case, returning decisions within hours but at denial rates substantially higher than human-reviewed decisions, the AMA's 2025 Prior Authorization Survey found. Physicians average 39 prior authorization requests per week, which requires 13 hours of staff time weekly to manage, and that workload lands directly on billing staff who are least equipped to absorb it during a period of turnover. Payers are running their own sophisticated AI systems to scrutinize claims in milliseconds. The behavioral knowledge an experienced biller holds about how a given payer adjudicates claims is being tested constantly and needs continuous updating just to stay accurate.
Policy change has widened the margin for error at the same time. The OBBBA has significantly changed Medicaid financing and eligibility, creating a high-scrutiny environment where the margin for error in documentation and medical necessity is non-existent. Navigating a shift of that size requires billers who understand not just what the new rules say on paper, but how each individual payer is actually implementing them in practice. A federal rule, CMS-0057-F, took effect January 1, 2026, and mandates seven-day standard decisions on prior authorization along with specific written denial reasons for Medicare Advantage and Medicaid plans, though ACA marketplace issuers on the federal exchanges face the denial-reason requirement without the seven-day timeline. The structured denial data this rule generates is only useful to a practice that has the expertise on staff to read it and act on it. State legislatures are adding their own layer: Washington state signed a law in March 2026 specifying that AI algorithms cannot be the sole basis for denying, delaying, or modifying a prior authorization, and any adverse decision made that way now requires review by a licensed health care practitioner. Rules this specific require billing staff who track policy changes in real time and absorb them into daily practice, not staff who learn about a rule change months after it took effect.
When the person who tracked all of this for a practice leaves, the practice does not return to where it stood before that person was hired. It is left navigating a payer environment that has grown more complicated than it was a year earlier, with less institutional context to make sense of it than the practice had the week before the departure.
The Performance Gap Between Well-Staffed and Understaffed Practices
A practice that holds onto its billing expertise outperforms one that cycles through staff on revenue cycle metrics, and the gap between the two represents meaningful recoverable revenue at a practice of almost any size.
Benchmarks for 2026 lay out that spread across specialties. Clean claim rate runs above 97 percent at best-in-class practices, against 92 to 96 percent for the average practice. Denial rate sits below 4 percent at best-in-class practices, while average practices run meaningfully higher. Days in accounts receivable stay under 24 days for best-in-class operations, while average practices carry noticeably more aged claims on the books. Net collection rate exceeds 96 percent among best-in-class practices, leaving average practices with a visible share of collectible revenue that never gets collected. First-pass resolution rate runs above 92 percent for best-in-class practices, while average practices resolve a smaller share of claims successfully on the first submission.
The specialty-level numbers sharpen the point further. Behavioral health practices average a denial rate of 14.6 percent, against a best-in-class figure under half that. Cardiology and orthopedics show similarly wide gaps between their average performers and their best performers. The distance between those two numbers, within the same specialty, is where institutional knowledge, or its absence, does its work. Roughly half of all denials trace back to front-end errors, things like eligibility checks, demographic mistakes, and insufficient authorizations, and eligibility problems alone account for a substantial share of the denials that were preventable in the first place. These are exactly the errors a biller who knows a payer's habits catches before the claim ever goes out. Initial claim denial rates have been climbing steadily through 2024, and that trend is projected to continue. The cost of running below best-in-class performance compounds year over year rather than staying fixed.
A practice looking at these benchmarks should read them as a diagnostic rather than a report card. The gap between average and best-in-class in a given specialty marks out how much revenue is sitting on the table, recoverable with the right institutional knowledge in place, which turns the question from "how bad is this" into "what would it take to close it."
Why Standard Responses to Turnover Fail
When a billing staff member leaves, most practices respond the same way: post the opening, redistribute the departing person's work among whoever remains, and onboard a replacement as fast as possible. Each of these steps addresses the number of people on staff, but none of them replaces the knowledge that left with the departing employee.
Redistributing work to remaining staff closes the coverage gap for a while, but it accelerates burnout among the people left carrying the extra load. RCM staffing analysis describes a self-reinforcing cycle: shortages produce burnout, burnout produces more departures, and those departures deepen the original shortage. Redistribution feeds that cycle instead of breaking it, because it treats the symptom, an uncovered task list, while adding more strain to the exact staff whose departure would cause the next round of damage.
Hiring a replacement restores headcount, but headcount is not the asset that was lost. A new hire arrives with general billing competence and none of the specific, accumulated knowledge about how this practice's payers actually behave. That knowledge has to be rebuilt from scratch, claim by claim and denial by denial, over months, while the practice absorbs slower processing, higher denial rates, and the same kind of preventable errors the departed biller would have caught before submission. The standard playbook restores a seat at the desk. It does not restore the map of payer behavior that made the previous occupant of that seat valuable, and until a practice treats that map as the asset actually at risk, every new hire starts the clock over again at zero.
Sources
- Healthcare Revenue Cycle Management Trends
- Surviving RCM Staff Shortages: Why Outsourcing Is the Smartest Move for 2026
- 5 states reforming prior authorization in 2026 - Becker's Payer Issues
- Prior Auth Denial Trends 2026: What's Driving Them, Which Payers Are Worst, and How Specialty Practices Fight Back